
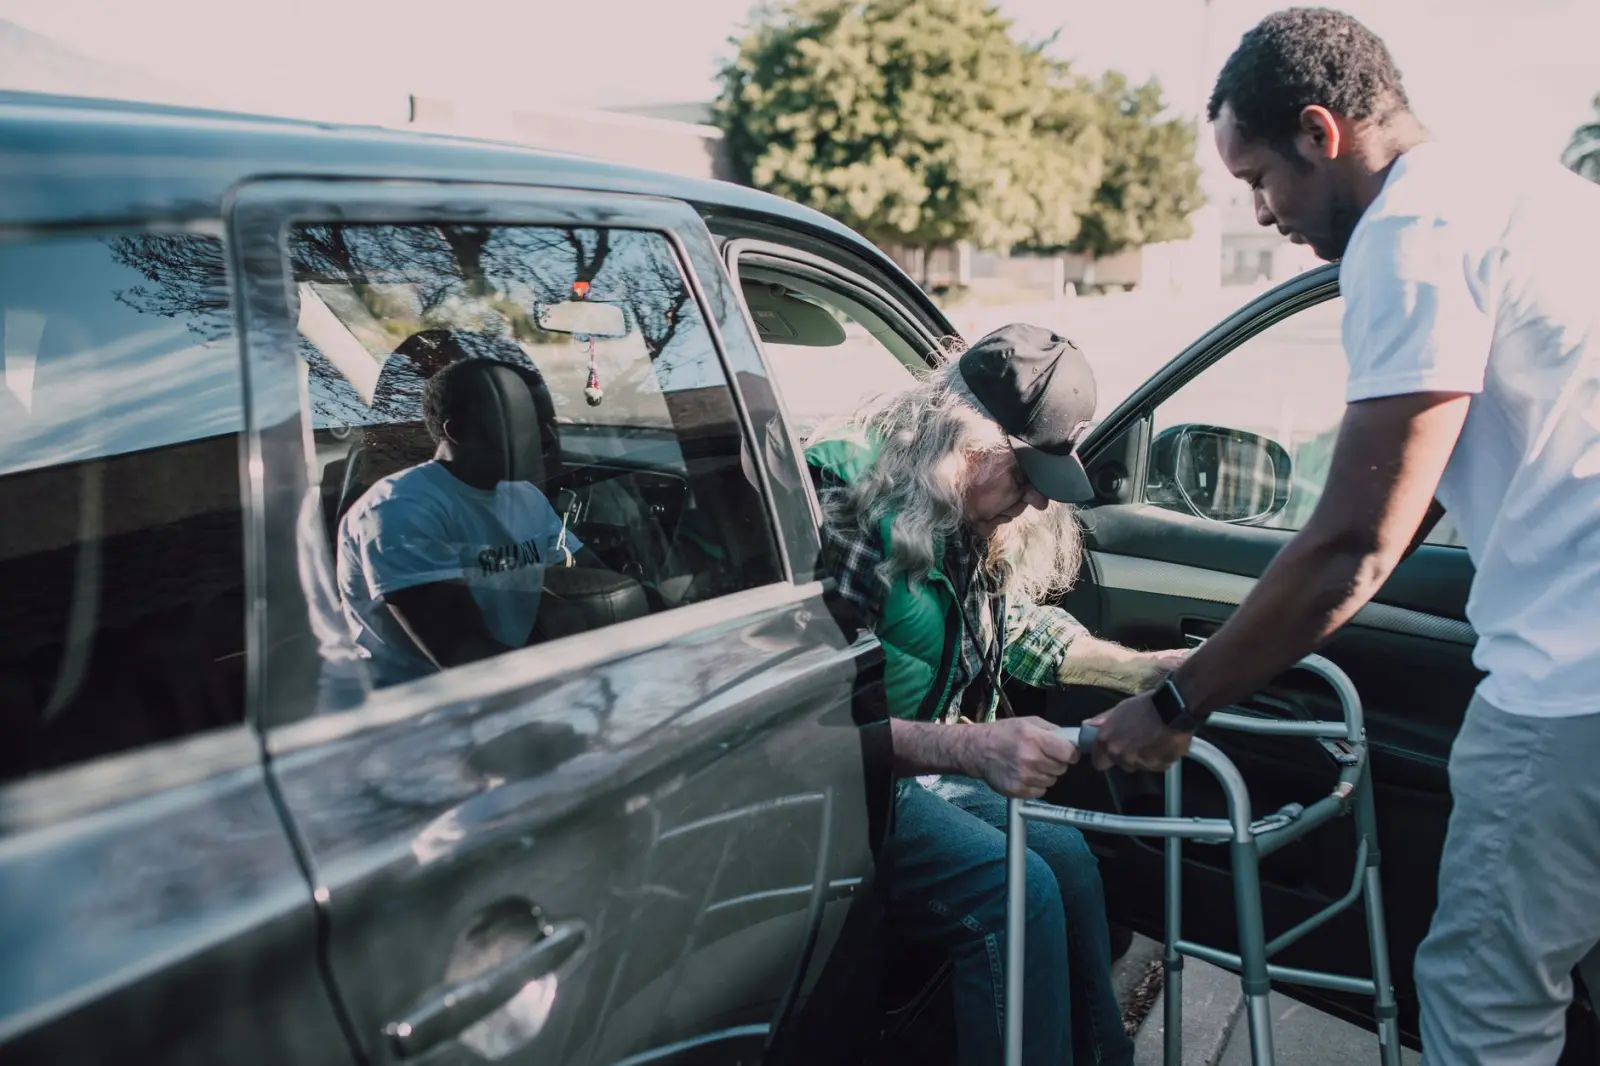
Over years of observing families and workplaces, I have noticed that caring responsibilities rarely arrive as a single, defined event. Instead, they accumulate through a series of small additions that feel manageable at the time but compound into something substantial. A parent starts helping an aging relative with one task – say, managing medications – and within months is handling finances, transportation, and medical appointments. A colleague becomes the unofficial mentor to a junior team member and gradually finds themselves responsible for training, emotional support, and career guidance. The expansion happens so gradually that the person often cannot pinpoint when things shifted.
This pattern occurs because caring work lacks the formal structure that other responsibilities have. When someone is hired for a job, there is a job description. When a student enrolls in a course, there is a syllabus. But when caring begins, there is usually just a need and a willingness. The willingness becomes the opening through which more requests flow. Each individual request seems small enough to accommodate, but the requests do not stop coming. They come because the person has already demonstrated capacity and availability, and because the person in need has no formal mechanism for requesting help – they simply ask when they need something.
The role of small, repeated requests
What I have consistently observed is that people rarely resist the first few additions to their caring load. The first time someone asks for help, it feels appropriate to say yes. The second time, it would feel unkind to refuse. By the fifth or tenth time, a pattern has been established, and both parties have come to expect that this person will provide this care. The person doing the caring may not have consciously agreed to take on an ongoing responsibility, but their repeated yes has created one.
This is different from a sudden, dramatic increase in responsibility. If someone’s parent had a major stroke tomorrow, the change would be unmistakable and would likely trigger a conscious decision about what care would look like. But when a parent’s mobility declines slowly, and the adult child gradually takes on more driving, more shopping, more household tasks, there is no clear moment of decision. Each addition feels like a natural extension of what they are already doing.
The same dynamic appears in professional settings. A teacher starts staying late to help one student understand a concept. That student tells a friend. Soon the teacher is holding unofficial tutoring sessions several times a week. The teacher may not have chosen to take on this role, but it has solidified through repetition and expectation. No one formally assigned it; it simply grew.
Normalisation and the shifting baseline
One of the most significant factors in this expansion is how quickly people adjust their sense of what is normal. Psychologists call this adaptation level theory, but I think of it more simply: we become accustomed to our current workload very quickly. If someone has been helping a family member for three months, that level of involvement begins to feel like their baseline. When they are asked to take on more, they are not comparing it to their original level of involvement – they are comparing it to what they have been doing for the past three months.
This shifting baseline is particularly powerful because it is invisible. A caregiver does not typically notice that their baseline has moved. They notice the new request, and they evaluate whether they can accommodate it relative to what they are currently doing. If they are managing the current load, the new request seems feasible. They do not feel the cumulative weight in the same way they would if they were comparing their current life to their life before they took on any caring responsibility.
I have observed this especially clearly in situations where someone takes on caring responsibilities while also working full-time or studying. The person may have started with five or six hours of caring work per week. After several months, they are doing twelve hours per week, but because the increase happened in small increments, they do not experience it as a doubling of their load. They experience it as a series of reasonable requests that fit into their schedule.
The absence of formal boundaries
Caring relationships typically lack the formal boundaries that structure other kinds of relationships. In employment, there are working hours, job descriptions, and performance reviews. In education, there are syllabi, grading rubrics, and defined learning outcomes. But in caring relationships, there is often no clear specification of what the care includes, how much time it should take, or when it should end.
This absence of boundaries creates space for expansion. If a parent does not explicitly define how much help they expect from their adult child, the adult child has no clear limit to work within. If a mentee does not have a formal mentoring agreement with their mentor, the mentee may continue to seek advice and support indefinitely. The caring person may want to set boundaries, but they often feel that doing so would be selfish or unkind, particularly if the person receiving care is vulnerable or in genuine need.
What I have found is that people who explicitly establish boundaries early tend to maintain more stable caring loads. This is not because they care less, but because they have created a structure that prevents the gradual expansion. A caregiver who says, “I can help with shopping on Thursdays and medical appointments,” has created a container for the care. A mentor who schedules a fixed time for mentoring meetings has created a boundary. These boundaries can be adjusted if circumstances change, but they prevent the unconscious expansion that happens when no boundary exists at all.
Recognition and its role in expansion
Another pattern I have noticed is that people often expand their caring roles because the care they provide is valued and appreciated. When someone is good at something, and that goodness is acknowledged, they tend to do more of it. A teacher who receives gratitude from a struggling student may find themselves spending more time helping that student. A family member who successfully helps resolve a crisis may be called upon to help with the next crisis, and the next.
This is not manipulation on the part of the person receiving care. It is simply that when someone demonstrates competence and willingness, they become the logical person to ask when a need arises. The caring person may not have intended to become the primary source of support, but their effectiveness has made them the obvious choice.
The expansion through recognition can feel positive in the moment. It feels good to be needed and to be good at something. But over time, as the volume of care increases, the positive feeling can shift to resentment or exhaustion. The caring person may begin to feel that their value is based solely on what they provide, rather than who they are. This realization often comes late, after the caring load has become substantial.
What I have observed is that the most sustainable caring relationships are those where the expansion is conscious and periodically reviewed. A caregiver might say, “I have been helping with these tasks for six months. Are we still on track, or has the situation changed?” This kind of check-in creates space for both parties to acknowledge what is actually happening and to adjust if needed. Without this kind of review, the expansion continues unexamined until someone reaches a breaking point.



